
Dr. Nicholas Norwitz, M.D. Ph.D., writes a best-selling science newsletter, StayCurious Metabolism, where he strives to empower readers with deep knowledge of cutting-edge health science.
Some of the foods I eat almost every day contain a saturated fat that new research suggests may help slow heart disease.
Yes, you heard me: a saturated fat that slows heart disease.
If you think that sounds bizarre, you better brace for what’s coming because it may leave you in a state of shock.
Let’s begin …
A Bacterium Linked to Healthy Hearts
The paper that will begin our journey was just published in Nature, one of the world’s top science journals.
The researchers began with a comparison: They analyzed the gut microbiomes of 223 healthy people and 189 people with cardiovascular disease, looking for bacterial species that differed between the two groups.
One species, Bacteroides uniformis (B. uniformis) stood out and was linked to better cardiovascular health; i.e., it was more abundant in healthy people and depleted in those with cardiovascular disease.
That is an association, and associations can’t prove cause and effect.
So, they went on to perform experiments to uncover whether there was actually a cause and effect relationship.
Now, the ideal test would be to give one group of teenagers this bacterium, give another group a placebo, and follow everyone for 30 years to see who develops heart disease. But that experiment will never happen. So, we turn to animals.
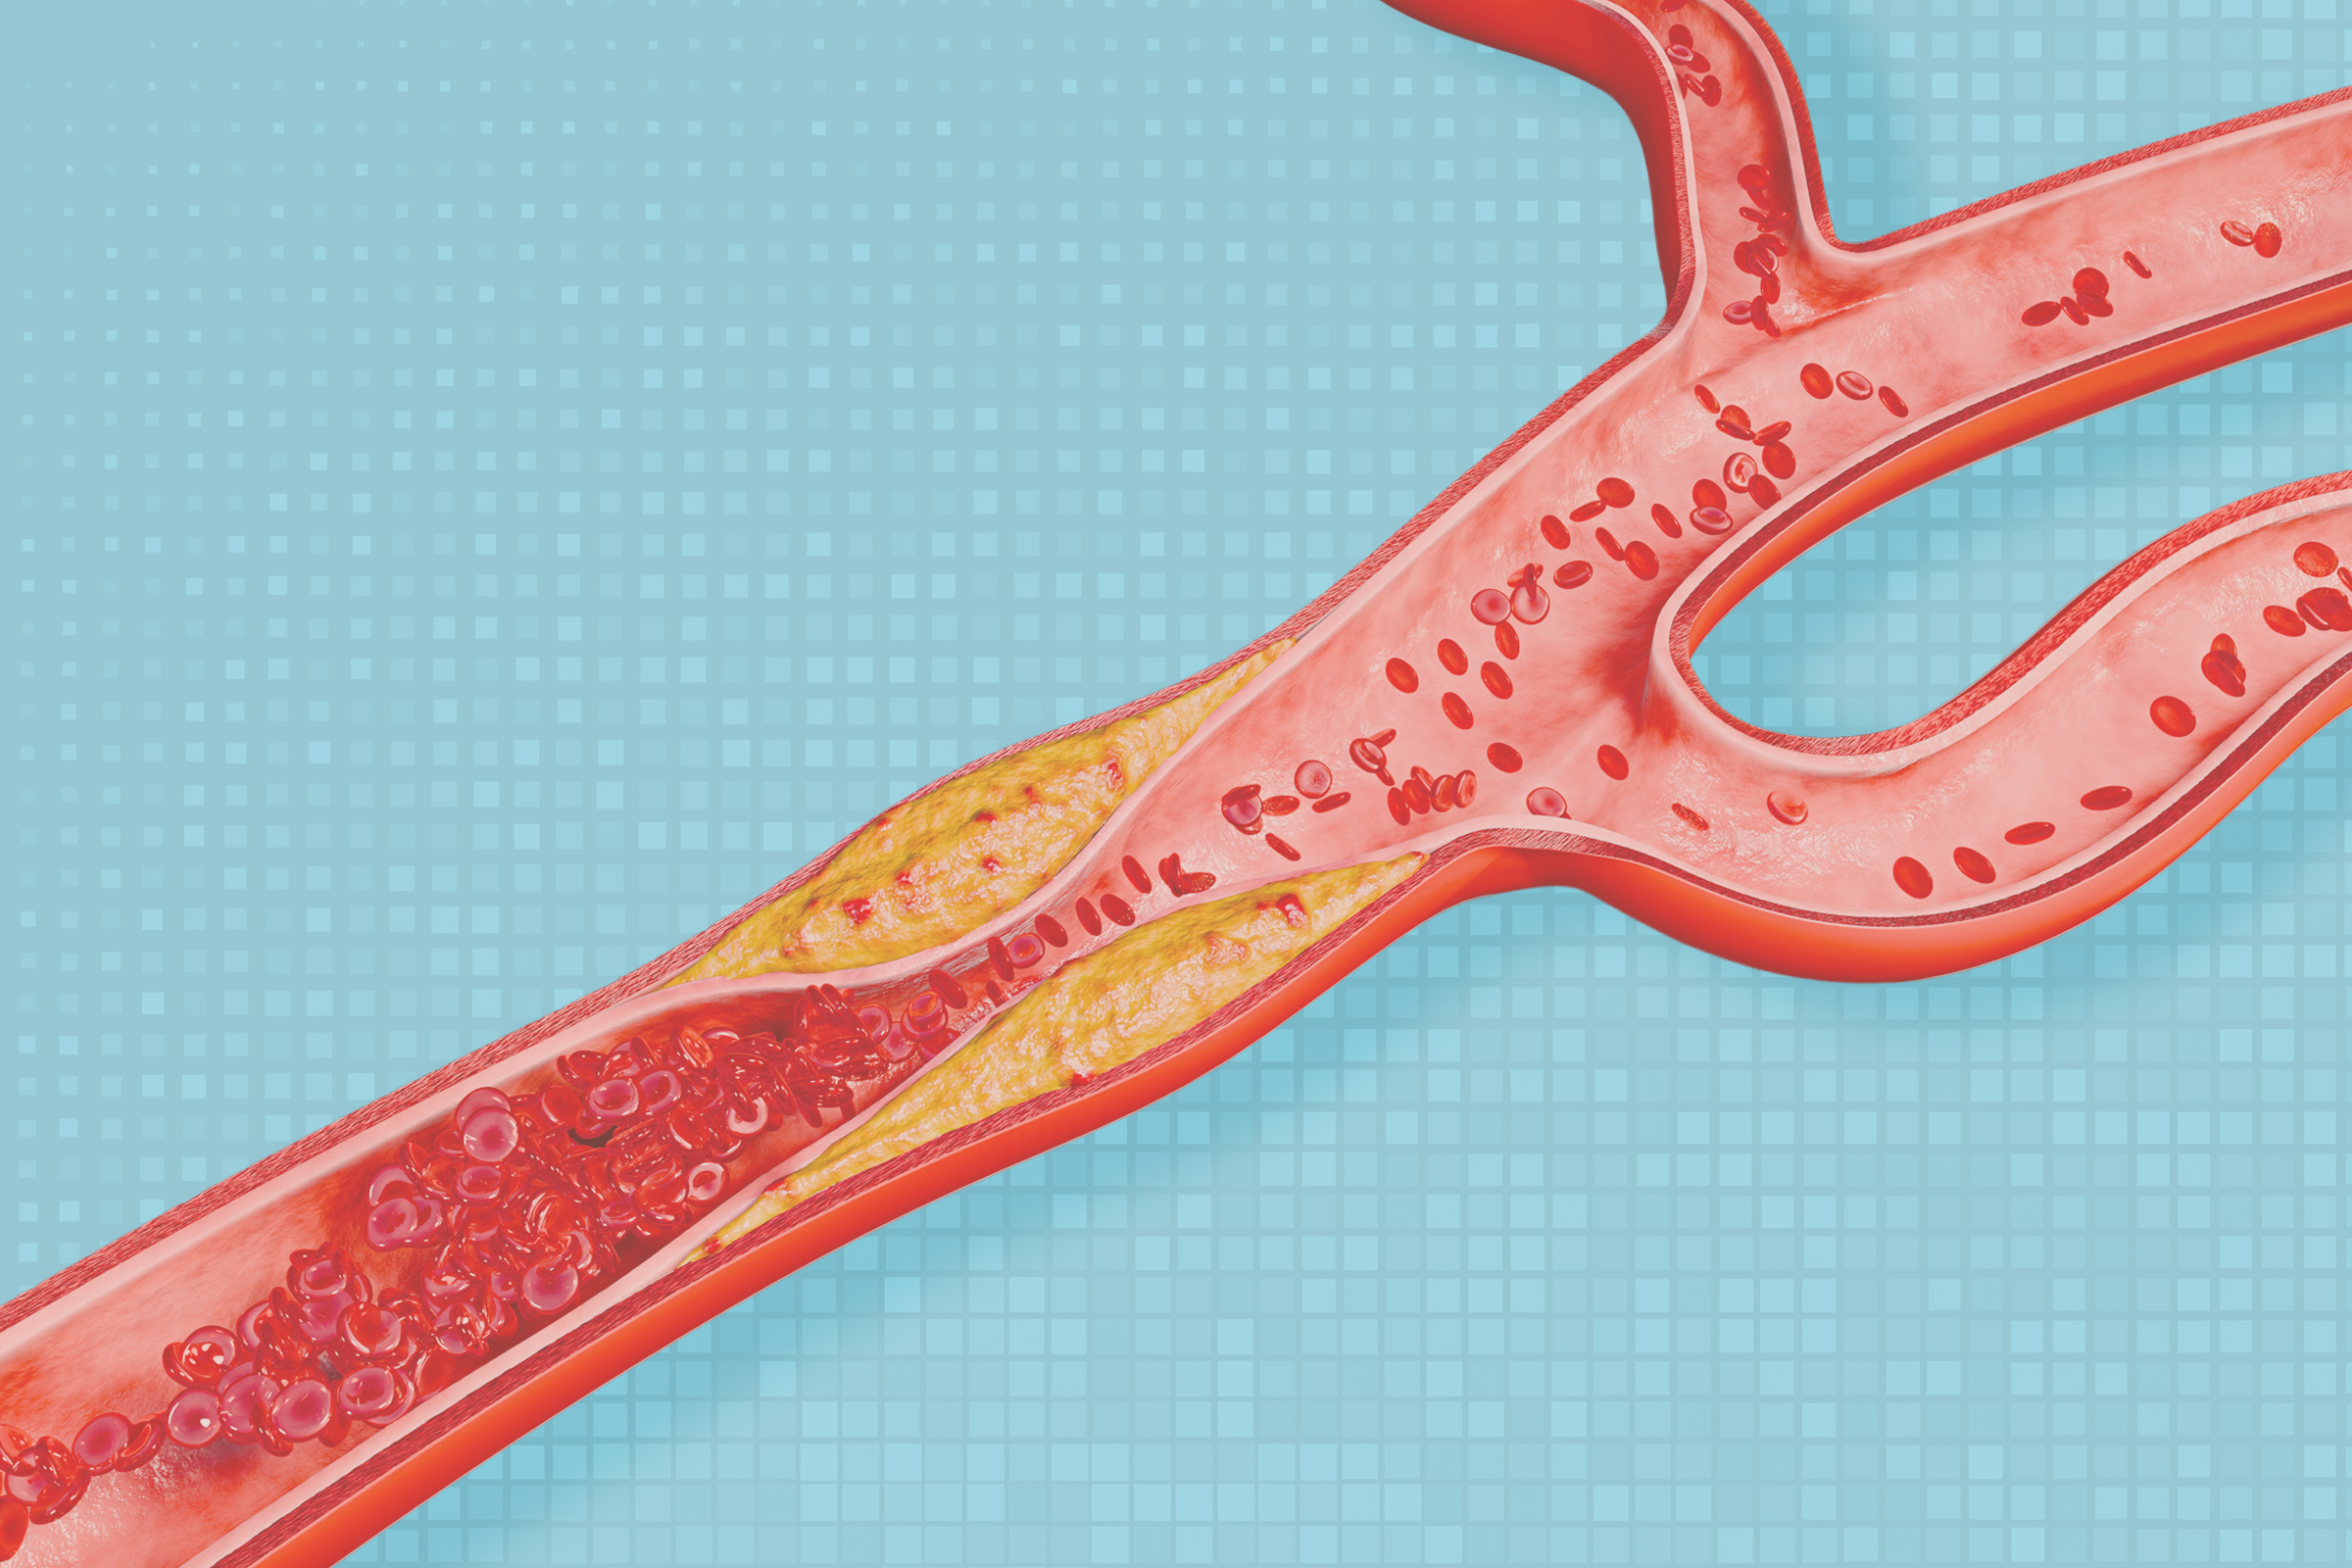
In this case, they used mice genetically prone to develop cardiovascular disease and fed them a high-fat, high-sugar diet for 12 weeks to stimulate the progression of atherosclerosis, the buildup of plaques in arteries.
Mice given B. uniformis developed substantially less arterial plaque than untreated mice. The effect was comparable to that of atorvastatin, a widely prescribed statin that the researchers used as a benchmark. The bacterium also reduced the number of inflammatory immune cells infiltrating the artery walls.
The story gets stranger.
How a Gut Bacterium Lowers Cholesterol
Not only was B. uniformis lowering inflammation, but it was also changing levels of fat and cholesterol in the blood, decreasing both triglycerides and LDL cholesterol, often called “bad” cholesterol.
But how?
The first clue came from the liver, which makes the majority of the cholesterol circulating in our blood.
The researchers found genes in liver cells involved in making cholesterol were turned down in the B. uniformis mice, and genes involved in pulling LDL out of the blood were switched on. The most important of these, for our purposes, was the gene that codes for the LDL receptor.
LDL receptors sit on the surface of liver cells and act like a catcher’s mitt, grabbing LDL particles from the bloodstream and pulling them inside. More receptors generally means less LDL in the blood. This is the shared endpoint of essentially every major cholesterol-lowering medication, including statins, ezetimibe, and PCSK9 inhibitors.
Digging further, the researchers found that the bacterium was suppressing cholesterol production inside liver cells. When a liver cell senses its own cholesterol is running low, it activates a master switch, which in turn builds more LDL receptors.
It’s as if the liver says, “I’m running low on cholesterol, so let me put out more catcher’s mitts to collect it from the blood.”
Still following?
Good.
Now, ready for something truly bizarre?
The specific step being blocked was an enzyme called HMG-CoA reductase. This is exactly the enzyme statins target.
In other words, a bacterium found in people with healthier hearts appears to signal the liver in a way that closely resembles a statin.
But wait, there’s more!
The Messenger Is a Saturated Fat
This raises an obvious puzzle. How does a bacterium in the intestines travel to the liver and steer it like a ship? The answer: it doesn’t—it sends a chemical message.
That message turned out to be a saturated fat called pentadecanoic acid, or C15 for short, since it is a saturated fat that is 15 carbons long. This fat gets taken into the blood, where it can reach the liver.
Put together, the chain of events looks like this:
A bacterium that is more common in people without heart disease produces C15.
That C15 saturated fat travels to the liver.
There, it inhibits the cholesterol-producing enzyme (the same one statins target).
This, in turn, prompts the liver to build more LDL receptors, which lowers LDL levels.
In mice, that translated into less atherosclerotic plaque and slowed progression of heart disease.
So, it appears our microbiome makes a saturated fat that works like a statin. How’s that for a biological plot twist?
LDL: 1 Part of a Larger System
Now, you’ll notice thus far I’ve only described biology, and not placed any value judgments on statins, saturated fat, or LDL cholesterol.
Obviously, this article isn’t meant to be prescriptive. However, we should address the elephant in the room: In humans, is LDL cholesterol really “bad” cholesterol?
The answer is more nuanced than yes or no.
The conventional model of atherosclerosis holds that LDL particles slip into the artery wall, get trapped there like flies in a spiderweb, and attract inflammatory cells that build plaque.
But LDL particles don’t act in a vacuum. Their behavior depends on the condition of the artery wall, which is shaped by blood pressure, inflammation, insulin resistance, and overall metabolic health. In an unhealthy metabolic environment, those factors can amplify LDL’s capacity to cause harm.
In a metabolically healthy person, these conditions are minimized or absent.
Stated concisely, LDL cholesterol isn’t “bad” cholesterol, end of story. But in a population that has a high prevalence of obesity, inflammation, and insulin resistance, LDL particles encounter an environment that collectively drives heart disease.
The solution, therefore, is to take a holistic picture and address multiple risk factors, rather than letting LDL and related markers such as ApoB become the singular focus of medical efforts.
Additionally, it’s worth remembering that interventions that lower ApoB, including statins, aren’t necessarily free of side effects or trade-offs. For example, controlled human studies have linked statins to increased insulin resistance and, in some settings, lower levels of the important metabolic hormone GLP-1. There’s also evidence suggesting that certain statins may impair mitochondrial function, although the full clinical consequences are unknown.
Interestingly, this raises the possibility that the statin-like effects proposed for C15 could differ in important ways. To date, there’s no evidence to my knowledge that C15 produces these same adverse metabolic effects.
But I digress.
What This Study Can and Can’t Tell Us
Now for the caveats. The cause-and-effect evidence here comes from mice. The human data show only that B. uniformis is more common in people with healthier hearts and depleted in those with cardiovascular disease.
There are good reasons to suspect the pathway also operates in people, since the bacterium tracks with heart health and the liver machinery involved is similar between mice and humans.
It would also be a mistake to conclude that “statins are natural.” As noted above, C15 and statins share a target, but they are different molecules, and different molecules can have different side effects.
Now, let me pay off the opening line.
Where C15 Comes From in Your Diet
C15 isn’t made only by gut bacteria. It has long been thought to come primarily from food, especially full-fat dairy and fatty fish.
How much might matter?
This study doesn’t tell us, but we can make some educated estimates from other controlled human trials (reviewed in this source letter) suggesting that somewhere between 200 mg and 300 mg per day may be enough to influence certain biomarkers.
With that range in mind, we can do some back-of-the-envelope math. You'd need about 50 grams of pecorino cheese, or somewhat larger servings of Parmesan, blue cheese, or about 150 grams of fatty fish, like mackerel and sardines—about 1.5 tins—to reach that dose.
What’s really my point here? Because it’s not to become a cheese addict—although some of you, like me, might already have this affliction.
A Nutrient Is Not a Food
We’re often told that saturated fat is uniformly bad for the heart, a view drawn largely from observational population studies that can be muddled by the huge diversity of people’s diets and metabolisms. Picture someone eating burgers and fries alongside a host of other unhealthy habits. The meat contains “saturated fat,” and saturated fat becomes the convenient scapegoat.
But “saturated fat” describes a large family of molecules with different properties, and each one arrives in a different food. Sardines deliver C15:0 alongside omega-3 fatty acids and high-quality protein. Cheese delivers it within a complex package of other fats, protein, calcium, and salt, and full-fat dairy is generally associated with neutral or beneficial cardiometabolic outcomes in research.
So, my practical takeaway is more modest than eating blocks of cheese in pursuit of a magic molecule: Don’t obsess over a single nutrient and miss the bigger picture. That’s where nutrition advice so often goes wrong. People grow afraid of isolated nutrients such as saturated fat or salt and end up avoiding perfectly reasonable whole foods, sometimes swapping them for heavily processed substitutes, all because they confused a nutrient with a food.
Yes, foods I eat almost every day contain a saturated fat that may help protect the heart. But I don’t eat sardines and pecorino in pursuit of a single molecule. I eat them because they’re nourishing and I enjoy them. Sometimes that’s reason enough.